
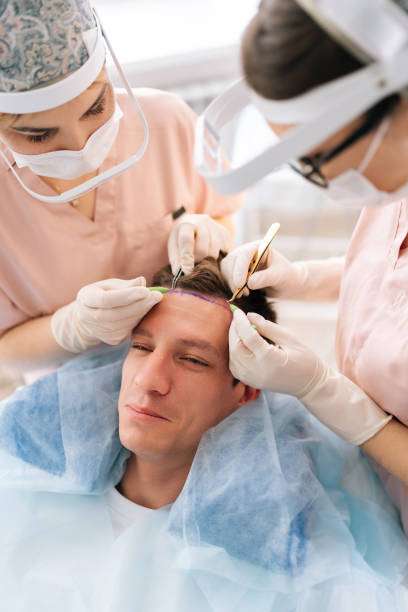

A receding hairline can change the proportions of the entire upper face, especially when the temples begin moving backward. Hair Transplant in Al Ain can restore lost frontal density by relocating healthy follicular units from a suitable donor area while preserving a natural transition between the forehead and existing hair.
The challenge is not simply filling an empty space. A convincing result depends on designing a hairline that suits the patient\’s facial proportions, age, donor supply and likely future pattern of hair loss.
For Dubai residents, this matters even more when appearance is part of a demanding professional or social lifestyle. The goal should be restoration that looks like your own hair rather than an obvious surgical correction.
Why a Receding Hairline Needs More Than Extra Grafts
The frontal hairline is an anatomical transition zone
The hairline sits at the boundary between the forehead and scalp. It is not a straight line, and it does not have uniform density from one temple to the other.
Natural frontal hairlines contain variation in follicular-unit size, spacing, direction and angle. Modern transplantation uses follicular units rather than large artificial-looking plugs, helping the surgeon reproduce these visual characteristics.
A good design therefore starts with the patient\’s existing anatomy rather than a predetermined template.
Temple recession changes facial proportions
When the temples recede, the forehead can appear wider even if the central frontal hairline has changed very little. Replacing every lost area with maximum density may look unnatural.
Instead, the treatment plan may concentrate on rebuilding the temporal corners and creating a gradual transition into the central hairline.
Age matters when designing the new hairline
A very low hairline may look attractive immediately after surgery but can become difficult to maintain if native hair continues to recede.
A more conservative design can leave enough donor resources for future treatment if additional hair loss develops. Current hair-transplant literature continues to emphasize patient selection, donor assessment and long-term planning as major parts of successful restoration.
How Hair Transplantation Can Correct Frontal Recession
Donor hair is selected for long-term value
The donor area is usually assessed around the back and sides of the scalp. The clinician examines density, hair caliber, follicular-unit characteristics and the stability of the donor zone.
This is important because donor hair is limited. Harvesting too aggressively can make the back or sides appear thinner.
FUE can reduce the linear scar associated with strip harvesting, but it does not mean the donor area is completely unaffected. Small extraction marks can occur, and excessive harvesting can produce visible donor depletion.
Single-hair grafts can help soften the frontal edge
The front edge of a hairline often benefits from finer follicular units. Larger multi-hair grafts can then be used farther behind the transition where additional density is appropriate.
This creates a gradual visual change rather than a dense wall of transplanted hair.
Hair direction is part of the design
Hair does not emerge from the scalp vertically. The angle changes across the frontal region and temples.
Recipient sites must therefore follow the surrounding hair pattern. Poorly designed angles can make otherwise healthy grafts look artificial. Clinical literature identifies recipient-site direction and hairline design as important technical factors in natural-looking transplantation.
What Patients Commonly Get Wrong About Receding Hairlines
“I only need the corners filled.”
Sometimes that is true, but not always.
A receding hairline may involve the temples, frontal forelock and areas immediately behind the hairline. Treating only the most obvious empty spaces can create an abrupt transition between transplanted and native hair.
The assessment should look at the entire frontal architecture.
“A lower hairline will automatically make me look younger.”
A lower hairline can change facial proportions, but lower is not automatically more natural.
The design should consider forehead height, facial shape, existing hair density and future loss. Hairline design literature specifically emphasizes matching the recreated border to the patient\’s donor supply and individual anatomy.
“FUE means there is no scarring.”
FUE does not mean completely scar-free surgery. Individual extraction sites can leave tiny round scars, although appropriately performed FUE can make these difficult to notice in many patients.
The quality of donor management remains important.
Clinical Planning for a Natural Frontal Result
For patients researching Hair Transplant in Al Ain, the consultation should focus on more than the number of grafts available.
Hairline position
The clinician considers the current hairline, facial proportions and likely future recession before marking the proposed border.
Temple shape
The temporal corners can have a major effect on how natural the restoration looks. They need to blend into the existing hair rather than create sharply defined corners.
Graft characteristics
Not every follicular unit is identical. Single-, double- and multi-hair units can have different roles within the restoration.
Donor preservation
A successful first procedure should not unnecessarily compromise the ability to manage future hair loss.
Native hair protection
If surrounding hair is miniaturizing, simply adding transplanted hair may not address the whole problem. Medical management may sometimes be discussed to help slow continuing native-hair loss. The American Academy of Dermatology notes that ongoing hair loss can continue after transplantation and that medical treatment may help preserve results.
Recovery and What Happens After Surgery
The early recovery period is not the final result.
Redness, mild swelling, crusting and tenderness can occur after transplantation. Patients should follow their individual postoperative instructions rather than judging the procedure by the appearance of the scalp during the first few weeks.
Temporary shedding can also occur. The American Academy of Dermatology reports that transplanted hair commonly sheds between about two and eight weeks after surgery before later growth becomes visible.
For Dubai residents, recovery planning should also account for strong sunlight, outdoor activities, swimming, gym sessions and international travel.
The transplanted follicles need time to progress through their growth cycle.
When the New Hairline Starts Looking Natural
Hair growth is gradual.
Most patients do not see the final outcome immediately. According to the American Academy of Dermatology, visible results commonly develop around six to nine months, although some patients may need up to 12 months.
The visual improvement also depends on how the native hair behaves around the transplanted region.
That is why a long-term plan is more valuable than simply counting grafts on surgery day.
Final Thoughts on Receding Hairline Correction
A receding hairline is one of the most visible forms of hair loss, but it is also one of the areas where surgical design matters most. The strongest planning combines facial proportions, donor preservation, follicular-unit selection, natural angles and realistic expectations.
For Dubai patients exploring advanced hair restoration and related aesthetic care, the wider services available through Tajmeels Clinic can provide a starting point for discussing an individualized treatment plan.


