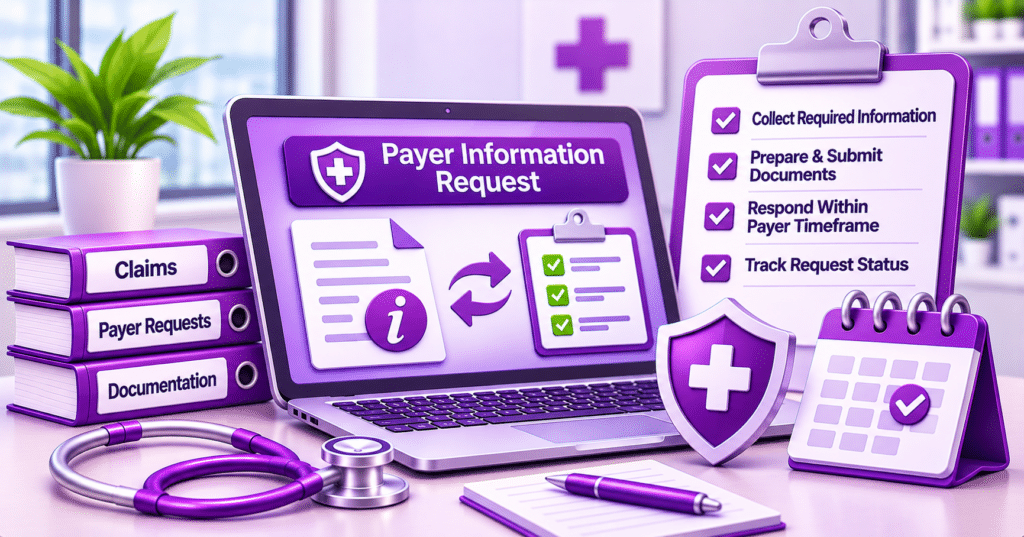

Payer requests for additional information can stop a medical claim from moving toward payment even when the initial submission passed basic edits. An insurer may need records, a clearer diagnosis link, an itemized charge, or proof that a service meets plan rules. Billing staff should treat each request as a tracked deadline, not an ordinary message. The most reliable approach starts with confirming the exact claim and the information being requested, obtaining appropriate documentation, sending it through the payer’s accepted channel, and confirming receipt. A defined workflow protects sensitive records and prevents avoidable delays.
Identify the Exact Payer Request Before Gathering Records
Not every request calls for a complete medical chart. Some insurers ask for an operative report, office note, invoice, accident details, or explanation of another payer’s responsibility. Staff should read the notice carefully and record the claim number, member identifier, date of service, requested item, response channel, and due date. If the wording is vague, seek clarification through the payer’s official support route rather than guessing.
Compare the request with the original claim and the practice management system. A discrepancy in units, provider information, or the billed procedure can reveal why the payer needs more detail. Make sure staff distinguish a documentation request from a formal denial or appeal; those statuses follow different processes. For example, an insurer asking for a signed clinical note is not necessarily disputing that the procedure occurred.
Consider a specialist claim for which the payer requests a procedure report. Before contacting the clinician, compare the requested service date and procedure with the claim image. A wrong date can lead staff to send the wrong report even when the correct chart exists. Confirm the requested date first, then request the specific signed document.
Coordinate Clinical and Administrative Evidence Safely
The billing team often cannot create the evidence a payer wants. It must work with clinicians, coding staff, medical records, and sometimes referral coordinators. Assign one person to request the exact document and set an internal deadline earlier than the payer’s deadline. Avoid asking a provider for an entire chart when a defined date range or encounter note would address the question.
Before release, check that the records belong to the correct patient and date of service, contain any necessary signatures, and correspond to the billed codes. Send protected health information only through approved secure channels in line with the practice’s policies and applicable requirements. If a record is incomplete, route the deficiency for legitimate correction or clarification; never alter a note simply to obtain payment.
A practice that coordinates medical billing services with its internal staff should document who owns source-data corrections and payer follow-up.
If a requested record is unavailable, document the reason instead of substituting an unrelated note. The practice may need to ask the payer whether another document is acceptable or whether the clinical team can supply an appropriate clarification. Record the answer and preserve the original documentation history. This keeps the response honest and helps later reviewers understand the limitation.
Submit Additional Information With a Clear Audit Trail
A strong submission includes a reference that allows the payer to match the records to the claim. That may mean a claim control number, attachment cover sheet, or payer-specific document identifier. Follow the instructions for upload, fax, electronic attachment, or mail; a document sent through the wrong route may never reach the claims examiner. Keep an internal copy of the submission record rather than relying on a verbal assurance.
Record who submitted the materials, the method used, the date, and any transmission or confirmation number. If several documents were sent, log each one so the team can answer a later question without searching multiple inboxes. When outside medical billing services assist, the practice should still define who can authorize disclosure and who owns clinical documentation.
Test one completed packet before considering the account resolved. Look for a readable attachment, matching patient identifiers, correct claim reference, and proof that the payer accepted the upload. A submission screen that closes successfully may not establish that a reviewer received the document. Save the actual confirmation in the claim note.
Monitor Payer Requests for Additional Information to Resolution
Submission is not the same as resolution. Set a follow-up date based on the payer’s stated review period and verify whether the information was attached to the claim. The status may remain pending while a specialist reviews a record. Distinguish a processing hold from a new denial, because appealing too early or resending the same document can create additional confusion.
When the payer says nothing was received, compare its preferred delivery method with the documented transmission details. Reattach only what is needed and keep the original history visible. If the request is closed without payment, obtain the specific adjudication reason and determine whether a corrected claim, reconsideration, or appeal is appropriate under that payer’s rules.
Use Request Trends to Improve Claim Readiness: Payer Requests For Additional Information
A practice should look beyond a single delayed account. Group requests by payer, specialty, procedure, missing record type, and originating work queue. Repeated requests for therapy plans, procedure reports, or accident details may show that the intake or documentation workflow needs a better trigger before submission. Review samples with clinical leadership rather than assuming every request is avoidable.
Useful measures include time from receipt to internal assignment, time to complete document gathering, and time until the payer acknowledges the response. These are operational measures, not promises of faster reimbursement. Use them to identify bottlenecks, update checklists, and teach staff what information can be collected correctly before a claim becomes stuck.
Conclusion
Payer requests for additional information require careful reading, secure coordination, and reliable follow-up. The goal is not to send as many documents as possible; it is to submit the right evidence for the right claim through the right channel. Practices that assign ownership, record deadlines, and monitor the payer’s next decision can reduce preventable administrative gaps. Reviewing patterns in payer requests for additional information also helps leaders improve documentation readiness without changing the clinical record solely for billing purposes.
Frequently Asked Questions (FAQs)
What is a payer request for additional information?
It is a request for records or details an insurer needs to continue reviewing a claim. It does not automatically mean the claim has been denied.
Who should answer an insurer documentation request?
Billing staff should coordinate the response with the clinical or records team that owns the requested information. The practice should authorize disclosure and track the deadline.
Can the same medical records be sent to every payer?
No. Submit the specific records requested through that payer’s accepted process and use appropriate privacy safeguards.
What if the payer says the documents never arrived?
Check the original transmission confirmation and claim reference first. Then verify the payer’s attachment instructions before resending.
How can practices reduce recurring requests?
Study the most common requested documents by payer and service. Update intake and documentation checks where those changes are clinically and operationally appropriate.